The inflammation that moves
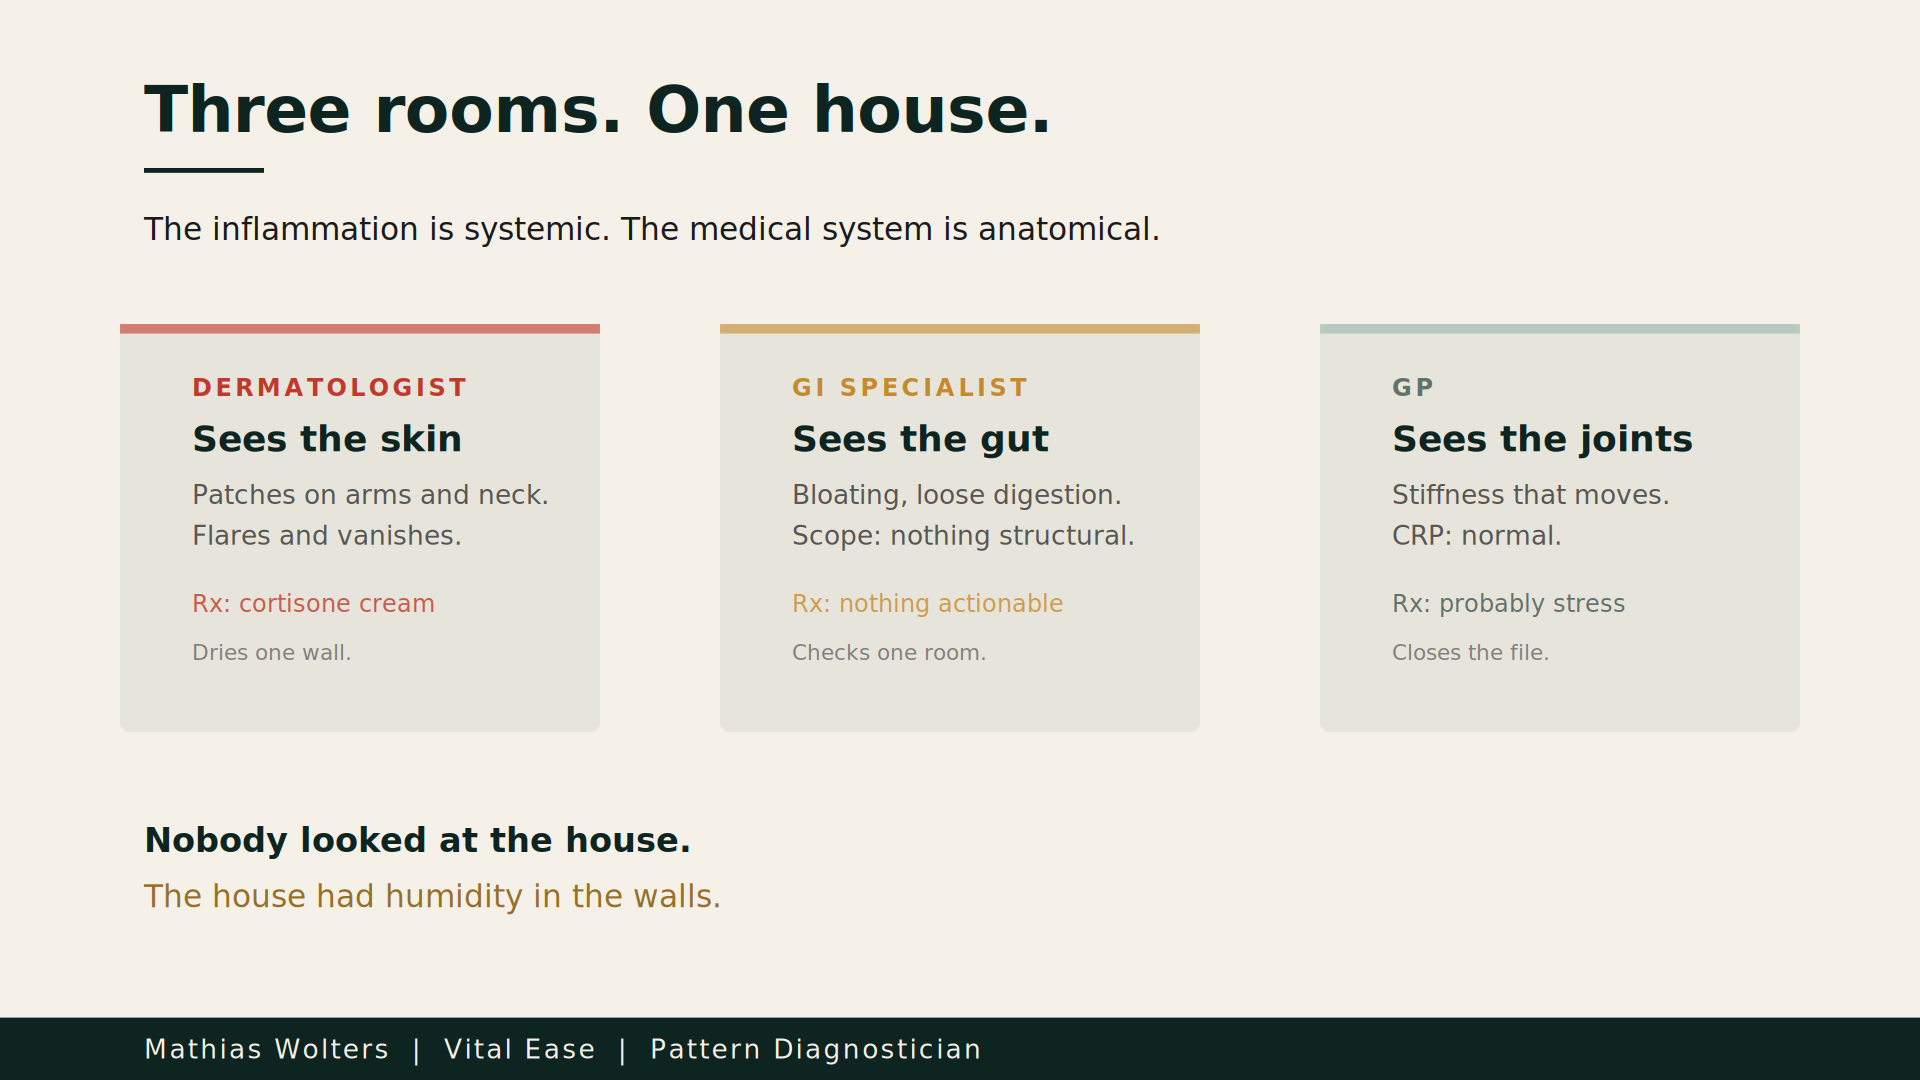
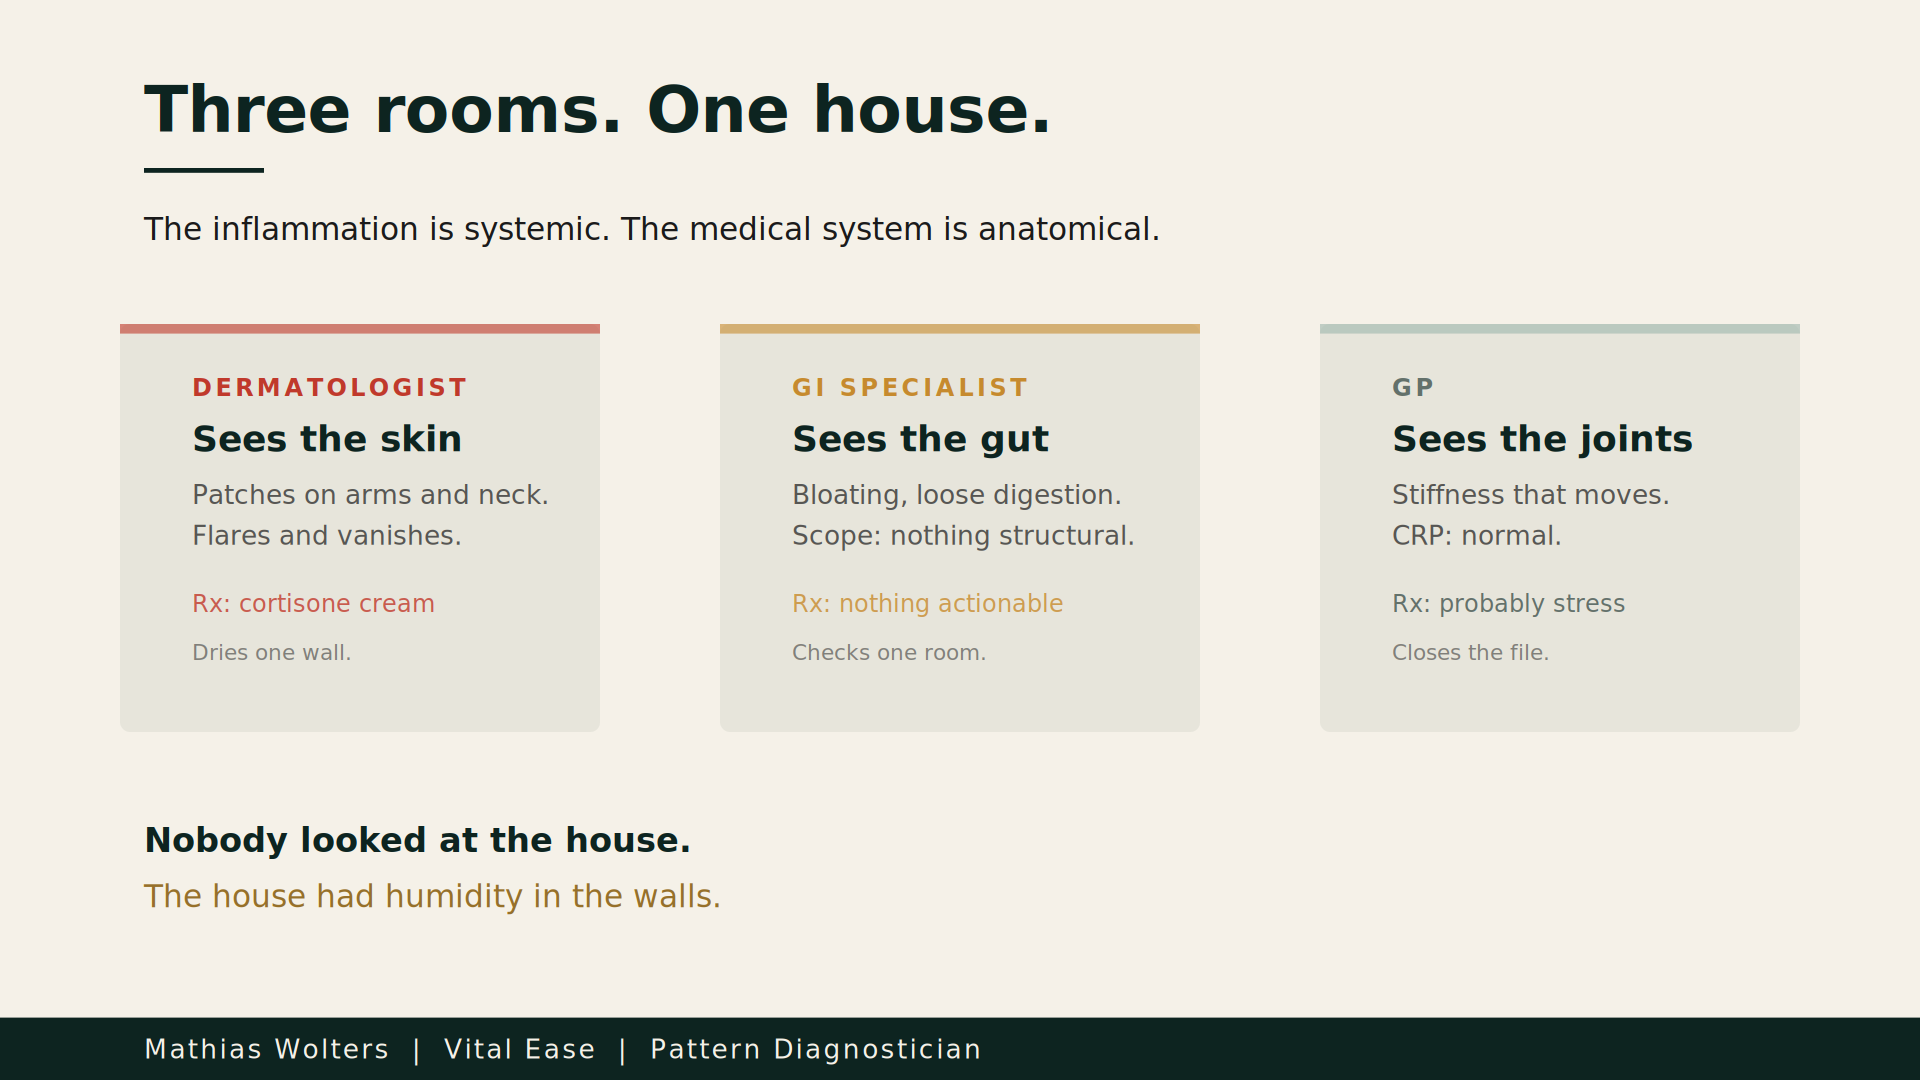
A founder came to me with a list of appointments. He had seen a dermatologist for the patches on his arms and neck that flared for a week, cleared, and came back somewhere else. He had seen a GI specialist for the bloating and the loose digestion that had been getting worse for two years.

A founder came to me with a list of appointments.
He had seen a dermatologist for the patches on his arms and neck that flared for a week, cleared, and came back somewhere else. He had seen a GI specialist for the bloating and the loose digestion that had been getting worse for two years. He had been to his GP twice for the joint stiffness that moved from knee to shoulder to hand and never stayed long enough to photograph.
Three specialists. Three locations in the body. Three separate conversations. The dermatologist gave him a cortisone cream. The GI ran a scope and found nothing structural. The GP ordered a standard CRP, which came back normal, and told him it was probably stress.
Nobody connected them, because each specialist owns one room in the house.
The house had humidity in the walls.
What this gives you
A way to understand why symptoms that move, flare, and vanish are not random and not in your head. They are one thing showing up in different places, and the reason nobody has connected them is that the medical system is built by location, not by pattern.
Here is the idea.
There are two kinds of inflammation. The first is structural. You tear a ligament, the knee swells, the inflammation stays in the knee because that is where the damage is. A specialist looks at the knee and finds the tear. That system works.
The second is systemic. Nothing is torn. Nothing is structurally damaged. The inflammation is circulating, driven from the inside by the gut wall, the immune system, and the metabolic state. It lands wherever the tissue is weakest that week. The skin one day. The joints the next. The head on Thursday. Then it lifts and you think it has gone, but it has not gone. It has moved.
You cannot pin it down because it is not in one place. And every targeted treatment, the cream, the joint injection, the elimination of one food, works in one room for a while and does nothing about the humidity.
Why standard testing misses it
Your GP probably ran a CRP. That test was built to detect acute inflammation, the kind that spikes hard during an infection or a serious autoimmune event. It is good at that.
Low-grade systemic inflammation sits beneath that threshold. It is not loud enough to trip the alarm, but it is constant enough to produce the symptoms you are living with. Your CRP comes back normal. The file closes. You are told it is stress.
The markers that catch it are different, and you have to ask for them by name.
hs-CRP. High-sensitivity CRP. Same molecule, finer resolution. It reads the low-grade fire that standard CRP is calibrated to ignore. If this is elevated even mildly, you have systemic inflammation running, and the conversation should change.
IL-6. Interleukin-6. One of the primary inflammatory signalling molecules. It tells you the immune system is actively producing the fire, not just reflecting damage somewhere. [VERIFY: availability of IL-6 testing in standard clinical settings vs specialist labs]
Intestinal permeability markers. Zonulin or lactulose-mannitol testing. These tell you whether the gut wall has become more porous than it should be, which is often where the whole cascade starts. A leaky gut wall lets fragments through that the immune system reacts to, and that reaction is what circulates. The skin, the joints, the brain fog. All downstream of a wall that is letting through what it should not.
Those three, alongside a standard panel, give you the picture that the knee specialist, the dermatologist, and the GI were each looking at one corner of.
Where the fire starts
Most of the time, it starts in the gut.
Not as a dramatic event. As a slow erosion. Years of processed food, too much sugar, too many refined carbohydrates with fat, irregular meals, food eaten fast and under stress. The gut lining weakens. The barrier that is supposed to be selective starts letting things through that should have stayed inside the tube.
The immune system, most of which lives along the gut wall, reacts. It produces inflammatory signals. Those signals do not stay local. They enter the bloodstream and circulate. They land in the joints and you get stiffness. They land in the skin and you get patches. They land in the brain and you get fog. They land in the connective tissue and you get the puffiness, the heaviness, the feeling of being waterlogged without a clear reason.
The founder I described had all of this. Neurodermatitis on his arms and neck. Overweight, not from overeating but from accumulation, puffy and heavy. Tired. No exercise because the body felt too heavy to move. Digestion weak and loose. And a diet that was feeding the fire, too much sugar and refined carbohydrates, too much fat alongside them, exactly the combination that drives the gut wall open further.
The cortisone cream suppressed the skin in one place. It did nothing about the humidity in the walls.
The humidity in the house
This is where the medicine I practise has its clearest structural advantage.
Imagine a house with bad ventilation. Moisture builds up. It does not stay in one room. It settles wherever the airflow is weakest. You can dry one wall with a towel, and the moisture appears on another wall the next week. You can dry that one too. You will be drying walls forever, because the problem is the ventilation, not the wall.
The ventilation is the conversion engine in the middle of you. When it is working, what comes in gets transformed into usable material and the residue gets cleared. When it weakens, the residue accumulates. It is heavy, it is turbid, it settles in different places, and it resists targeted treatment because it is not in one place.
When that residue sits long enough, it heats up. The heavy accumulation becomes hot accumulation. That is when the skin flares, the joints burn, the puffiness gets worse, and the brain fog thickens. You are carrying something that is both heavy and hot, and it moves because it is circulating, not fixed.
That picture, the heavy hot residue circulating in a system whose conversion engine has failed, is one of the most common patterns in the tradition I trained in. Chinese Medicine has been reading it for a very long time, and the approach is specific. You do not chase it room by room. You rebuild the ventilation and clear the residue from below.
What we did
We changed his diet first. Cut the sugar, cut the refined carbohydrates, dropped the fat-and-carb combination that was feeding the fire. Warm, cooked, simple food. Protein at every meal. Nothing cold, nothing raw, nothing that costs the system work before it delivers value. This was not a restriction diet. It was matching the input to what the engine could actually handle.
He started walking. Every day, thirty minutes, nothing harder than that. Not to burn fat. To move the circulation so the residue stops settling in the same places. Movement is how the body clears what has accumulated, and a depleted system cannot clear anything while sitting still.
Chinese herbs did the structural work. Warming the centre, strengthening the conversion, and clearing the heavy hot residue in layers. Not all at once. The residue has been building for years and forcing it out fast in a weakened system makes things worse. It comes out in an order, and the order matters.
Targeted supplements alongside the herbs to support what the gut wall needed to rebuild. Not a stack of fifteen bottles. A few things, matched to the picture.
The skin cleared first. Then the puffiness dropped. Then the joints quietened. Then the energy came back, and he started moving more because the body no longer felt like it was carrying water in every limb.
The cortisone cream stayed in the drawer.
What you can do this week
If you have symptoms that move, flare, and vanish, and nobody has connected them, start here.
Get the right markers. Ask for hs-CRP and a full inflammatory panel at your next blood draw. If your doctor only offers standard CRP, ask for the high-sensitivity version specifically. That one test changes whether the fire is visible or invisible on paper.
Look at your gut. If you have bloating, loose digestion, or heaviness after eating alongside the moving symptoms, the gut wall is where the investigation should start. Ask about intestinal permeability testing. The connection between a leaky gut and systemic inflammation is not alternative medicine. It is well-documented immunology that most GPs do not test for because it falls between specialties.
Stop feeding the fire. Cut the sugar for one week. Drop the refined carbohydrates. Eat warm, cooked, simple food. This is not a cure. It is removing the fuel. If the skin calms and the puffiness drops inside seven days, you have your answer about where the fire is being fed from.
Move. Walk every day. Thirty minutes. Not to exercise. To circulate. A body that sits still while carrying systemic inflammation is a house with the windows closed while the humidity builds.
Before you close this
If you have been to three specialists and nobody connected the picture, you are not a difficult case. You are a systemic case being read anatomically. The knee specialist sees a knee. The dermatologist sees skin. The GI sees a gut. Nobody sees the humidity in the walls, because nobody is looking at the house.
The fire is not in your knee, your skin, or your gut. It is circulating. And it has a source, which is usually the gut wall, fed by what you put in and driven by a conversion engine that stopped clearing what it should.
Stop drying the walls one by one. Fix the ventilation.
Mathias
P.S. The Sovereign Biological Audit reads 40 markers across eight biological systems against functional optimums rather than population averages. It finds whether systemic inflammation is running, where the gut barrier stands, and what the conversion engine is actually doing. That is the whole-house read that the room-by-room specialists cannot give you. vitalease.co/sovereign-biological-audit